Fuelling for a Marathon: Our Expert Tips for Race Day

Liam McVarnock

Pain Flare-Ups Don't Mean You're Getting Worse

Fueling for a Marathon: Our Expert Tips for Race Day

You trained hard for months. Now it's time to show off that work. But there’s one last piece of the puzzle that could make - or break - your race day: fueling.

You nail your training runs, dial in your pacing, and get your shoes just right... only to fall apart at mile 18 because your energy tank hits empty.

Or worse yet - you over-carb-load with unknown foods and find yourself at kilometer 20 praying to the race gods for a porta potty to appear because you’re in serious danger and about to blow. (Unfortunately, I’m speaking from experience here.)

Let's make sure that doesn't happen, folks. Here’s how to fuel smart - before, during, and after your 26.2-mile journey.

Why Proper Marathon Fueling Matters

Every marathon runner fears hitting the wall. That crash usually happens when your glycogen stores - your body's carb fuel tank - run dry. Imagine speeding down the highway, pedal to the metal, only to realize your tank’s on empty. No good.

Smart fueling helps:

  • Maintain steady energy
  • Delay fatigue
  • Minimize porta potty emergencies
  • Optimize endurance performance
  • Impress your raving fans on Strava

Bottom line: Training gets you to the start line. Fueling gets you to the finish line.

What to Eat Before Your Marathon

A. Carb Load: 48 Hours Before

Shift your focus to high-carb, low-fiber, easy-to-digest foods:

  • White rice
  • Pasta
  • White bread
  • Peeled potatoes
  • Fruit juice
  • Sports drinks
  • Bananas

You can sprinkle in fun foods like candy or pretzels — but if you’re not used to eating tons of sugar, be cautious. (Sour patch kids disaster, anyone?)

Aim for 7–12g of carbs per kg of bodyweight per day.

Example:
60kg runner (~132lbs) → 420–720g carbs/day.

Fast, simple carbs = faster glycogen storage. Fiber and fat = slower digestion. You want a quick pit stop, not a traffic jam.

B. Race Morning Nutrition

Race day breakfast is critical. Overnight, your body burns through liver glycogen - and you need to top it up.

When you eat carbs, they break down into glucose and fructose:

  • Glucose refills muscle glycogen.
  • Fructose refills liver glycogen.

That's why eating foods that contain both glucose (white toast) and fructose (jam or a glass of OJ) can help top up both of these sources to maximize your performance at the race.


How Fructose and Glucose Help You Race Better

Picture this:

90 cars 🚗 all merging into one bridge = traffic jam. That’s what happens when you only eat glucose.

But fructose uses a different bridge.

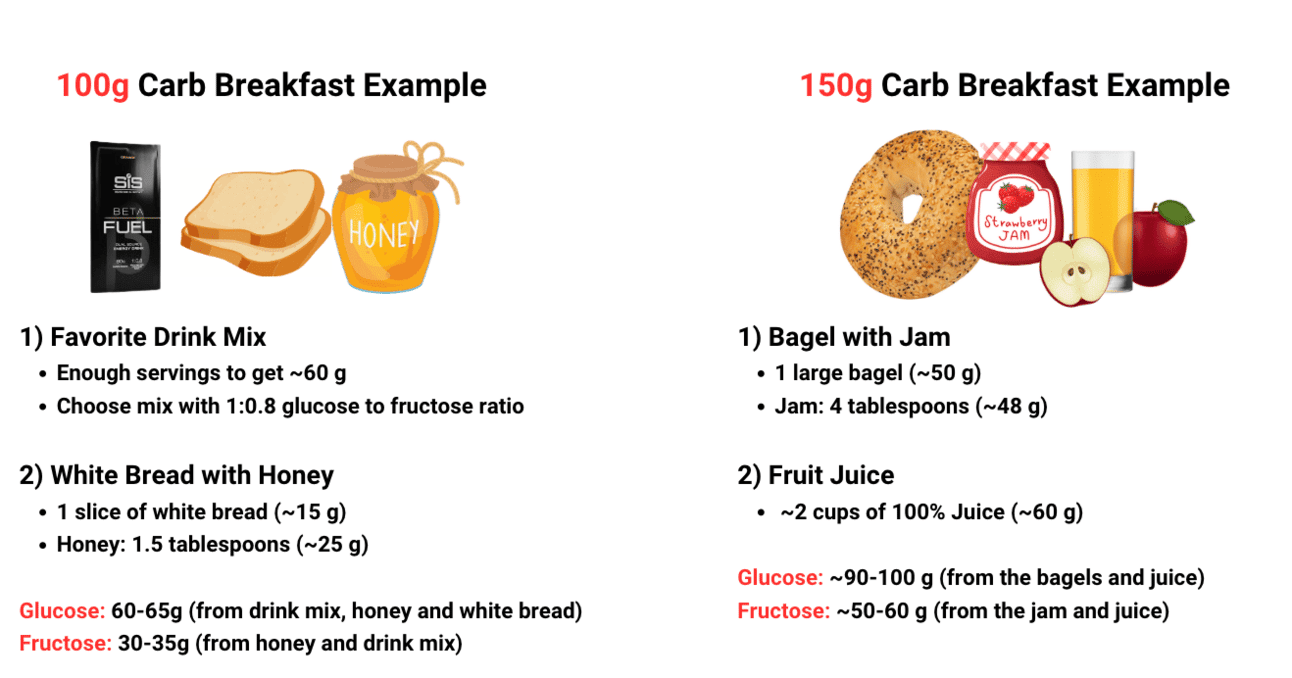
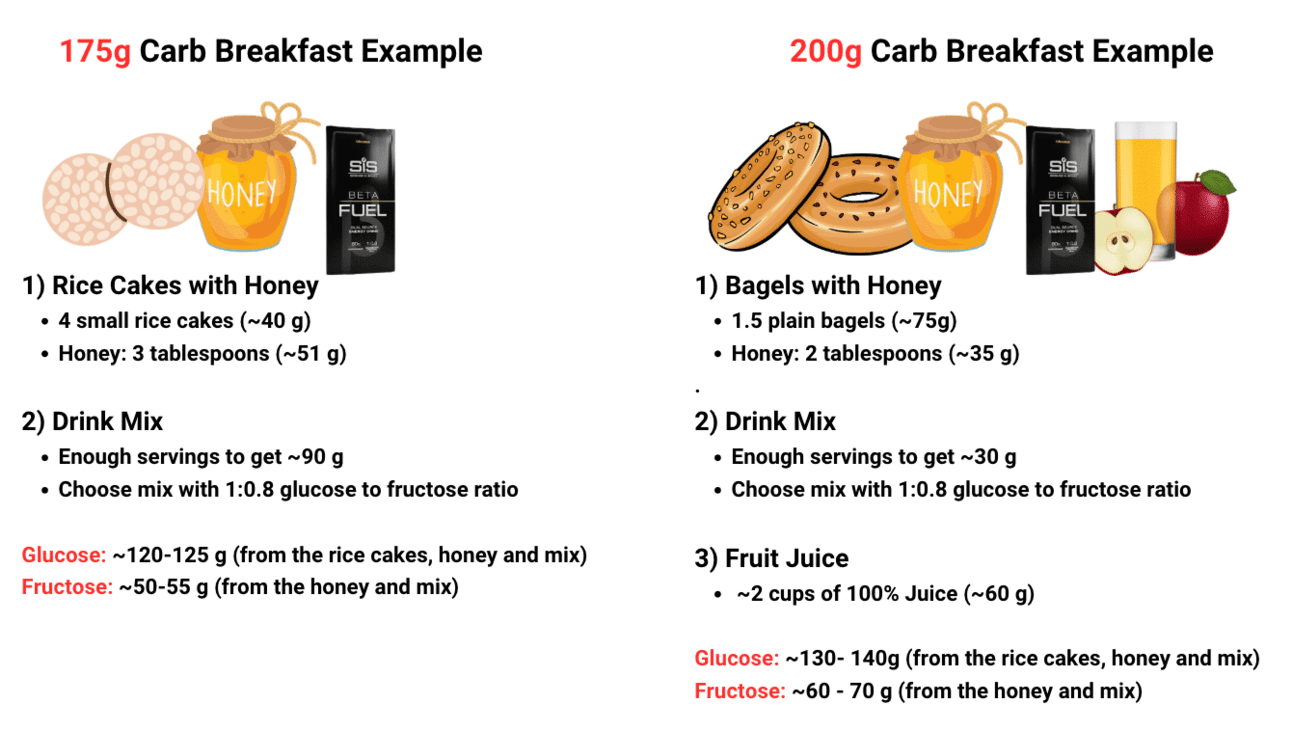
Use both at once, and you open up two lanes - more carbs absorbed, faster, without the backup. That’s why race breakfasts aim for a 2:1 glucose-to-fructose ratio (like rice cakes + honey or bagels + juice).
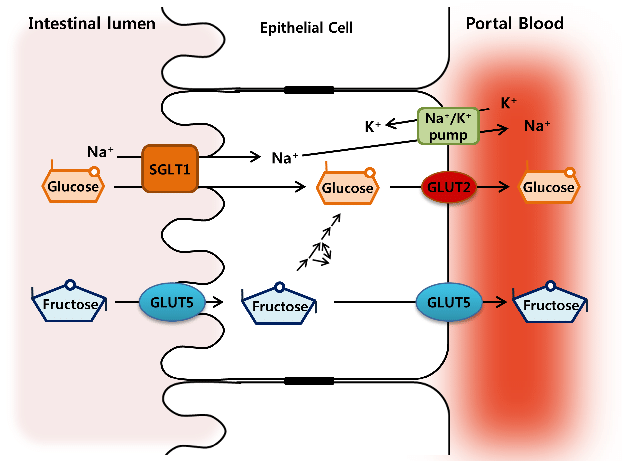
glucose fructose transporters for race day fuelling for your run

 (If this diagram looks like scientific jargon, don’t worry. It does to me too. Just remember: two separate lanes. More fuel, faster delivery.)

How Much to Eat Before the Race

✅ 2–4g of carbs per kg, 2–4 hours before your start time.

Bodyweight (kg) Bodyweight (lbs) Low Rec (g carbs) High Rec (g carbs)
50 110 100 200
60 132 120 240
70 154 140 280
80 176 160 320
90 198 180 360
marathon fuelling options
marathon fuelling breakfasts

Stick to familiar, easy-to-digest carbs:

  • Rice
  • White bread
  • Bagels
  • Jam, honey
  • Juice
  • Drink mixes

Race day is not the time for bacon, broccoli, or "let’s just wing it." Stick to what you know.

What to Eat During the Race

Fuel early and often - don't wait until you’re running on fumes.

Target 30–90g carbs per hour, depending on size, pace, and gut training.

Fueling strategy tip:
Smaller, frequent sips and bites (e.g., 250ml fluid + 20g carbs every 20 minutes) beat chugging a giant carb bomb all at once. Practice this during long runs. Gut training matters as much as leg training.

Good options:

  • Gels
  • Chews
  • Sports drinks
  • DIY carb mixes

Hydration and Electrolytes

Staying hydrated is important. Dehydration by just 2% of your body weight can cause a drop in performance. For a 200lb person that's just a 4lb drop!

And here's the kicker: Those fancy $300 carbon-plated shoes? They might give you a 3–4% boost. Neglecting hydration is like stepping over a $1 bill to pick up a Quarter. Doesn’t make sense.

Hydration tips:

  • Aim for ~400–800ml (13–27 oz) of fluid per hour during the race, adjusting for heat and humidity.
  • Include 300–600mg of sodium per hour as a starting point.
  • Heavy sweaters (salt stains on clothes) may need up to 1000mg/hour.
  • Use sports drinks, salt tabs, and salty gels to cover both fluid and electrolyte needs.

If you're only drinking water without replacing electrolytes, you risk hyponatremia (low blood sodium) - especially in hot conditions.

Post-Marathon Recovery

You just ran a marathon. Your body is wrecked and needs nutrients fast.

In the first 30–60 minutes post-race, focus on:

  • Carbs to refill glycogen
  • Protein to repair muscles
  • Fluids and electrolytes to rehydrate

Simple tip: You burn about 1 calorie per kg per km — for example, I’m 87kg and burn roughly 3600+ calories during a marathon. To replace those calories, I’d aim for 900–1200g of carbs spread across the day.

Dialing in your fueling strategy isn’t just for elite athletes. If you want to race stronger, feel better, and recover faster, Ludus Wellness can help you build a customized endurance fueling plan. Plus, Vital’s endurance coaching can help you pair the right training and nutrition together for maximum results.

Want to learn more? Click here to check out our Nutrition Coaching — or click "Book Now" to schedule your call with the Ludus team today.

More About The Author

More About The Author

Liam McVarnock is the founder of Ludus Wellness, a Calgary-based nutrition coaching company built for high performers who feel out of shape and low on energy, but don’t have time to waste.

Their coaching team have helped over hundreds of time poor clients lose fat, rebuild energy, and feel in control of their health again — without giving up their careers, families, or lifestyle. Many go on to conquer physical milestones they never thought possible: running 10Ks, completing marathons, skiing full days in the Rockies, and beyond.

Outside of coaching, Liam leads from the front: completing double Ironman-distance triathlons and chasing a sub-3-hour marathon — proving what’s possible when your body is trained and fueled with purpose.

Introduction

"Oh, it's just part of getting older."

Cool, cool, cool. Except your shoulder used to work fine. You used to jump out of bed. You weren't rehabbing a new injury every other week. So no, this isn't just a normal part of aging, and it doesn't have to be something you just accept.

There's actually a clinical name for it: the musculoskeletal syndrome of menopause. It's our understanding of how the hormonal changes of perimenopause and menopause affect the musculoskeletal system, and how hormone therapy can be used to help treat these symptoms as part of a holistic approach to rehabilitation.

The same hormonal changes that cause our hot flashes, disrupted sleep, and make us not feel like ourselves are also directly impacting the tissue that lets you move: how your muscles repair themselves, how your joints handle load, how your tendons hold up over time, and how your bones maintain their density and strength.

This article breaks down what's actually happening in your body during perimenopause and menopause, why declining estrogen hits your musculoskeletal system so hard, and how a collaborative approach between hormone therapy and rehabilitation can improve your quality of life.

Not sure if hormones are behind your aches and pains?

A hormonal health consult with Pause Health can tell you whether hormonal changes may be part of the picture, and whether hormone therapy is appropriate for you. A movement assessment with Vital Performance Care tells you what's actually happening with your strength, mobility, and joints. The real answer often needs both.

Book a Hormone Consult with Pause Health

Book a Clinical Musculoskeletal Assessment with a Chiropractor or Physiotherapist at Vital Performance Care


What Is the Musculoskeletal Syndrome of Menopause?

The term was formally introduced in 2024 by orthopedic surgeon Dr. Vonda Wright and colleagues, in a review published in the journal Climacteric (Wright et al., 2024). It covers the cluster of musculoskeletal symptoms that show up as estrogen declines during perimenopause and menopause:

5 common symptoms of menopause

"Common doesn't mean normal, and it doesn't mean untreatable."


Why This Gets Missed

40% of women menopause

Imaging isn't always helpful here, and a normal scan doesn't mean nothing's wrong. It usually means a single joint in isolation isn't the whole story.

If you're in midlife dealing with shoulder pain, recurring tendon issues, stiffness, or a real drop in strength, the useful question isn't just "what's wrong with this joint." It's what else has changed:

menopause checklist


All of it can be part of the same picture, and all of it is worth bringing up with your provider.

It's Not Only a Post-Menopause Problem

These changes often don't wait for your final period to show up. For a lot of women, this starts in perimenopause, while hormones are still fluctuating rather than non-existent. New stiffness, more frequent tendon flare-ups, muscle that's harder to maintain, an injury that seems to have come out of nowhere — these can all start years before menopause or the one-year anniversary of your last menstrual period.

menopause symptoms

That doesn't automatically mean hormones are the cause, but when it's happening alongside other perimenopause symptoms, it is worth considering the connection. Waiting until you're fully postmenopausal to start paying attention also means missing a window where building strength and addressing risk factors is a lot easier than trying to recover ground later.

How Estrogen, Progesterone, and Testosterone Affect Your Joints, Muscles, and Bones

Your musculoskeletal system is more hormone-sensitive than most people realize. Estrogen, progesterone, and testosterone receptors exist throughout your muscles, tendons, ligaments, cartilage, and bone. When those hormone levels shift, so does the health of every one of those tissues.

menopause list


Estrogen: The Primary Driver

Estrogen plays several distinct roles that matter for your joints and muscles:

1) Muscle repair and growth.

Estrogen supports the satellite cells responsible for repairing and building skeletal muscle. As estrogen declines, muscle protein synthesis becomes less efficient, contributing to the accelerated loss of muscle mass and strength seen after menopause (Critchlow et al., 2023; Hansen, 2018).

2) Inflammation control.

Estrogen has anti-inflammatory effects on muscle and connective tissue. Lower estrogen is associated with higher baseline inflammation, which can show up as generalized aches, tendon irritation, and slower recovery from exercise.

3) Bone density.

Estrogen slows the rate of bone breakdown. Its decline is the single biggest driver of the rapid bone loss that happens around the final menstrual period, which is why osteoporosis risk climbs so sharply in this window (Karlamangla et al., 2021).

4) Collagen and connective tissue.

Estrogen supports collagen production in tendons, ligaments, and cartilage. Research measuring tendon tissue directly has found that postmenopausal women on estrogen therapy have higher tendon collagen synthesis rates than those who aren't (Hansen, 2018), meaning their tendons are literally better equipped for ongoing repair. This is part of why frozen shoulder and tendon injuries become more common in this stage.

Progesterone: An Underexplored but Meaningful Role

Progesterone gets far less research attention than estrogen when it comes to musculoskeletal health, but it isn't inactive. It has a calming effect on the nervous system that influences sleep quality and pain perception, and both poor sleep and heightened pain sensitivity make other MSK symptoms feel worse. That alone makes progesterone relevant to how you feel day to day.

There's also emerging research on progesterone's more direct role in connective tissue. Progesterone receptors have been identified in tendon tissue, and some research suggests progesterone may support collagen synthesis rates in muscle in postmenopausal women (Hansen, 2018). At the same time, animal studies have shown progesterone can increase the expression of relaxin receptors in ligaments and tendons, which theoretically could make tissue more responsive to joint-loosening effects, though this evidence is largely limited to rodent models rather than human studies. Put simply, the current research suggests progesterone has a mixed, tissue-dependent effect, and the science is still catching up to what's seen clinically.

What is well established is that progesterone works alongside estrogen rather than independently, and has anti-inflammatory properties of its own. So as progesterone declines during perimenopause, you're losing more than estrogen's protective effects — you're also losing progesterone's contribution to sleep, pain modulation, and inflammation control.

Testosterone: Relevant Beyond Libido

Testosterone is routinely mislabeled as a "male hormone," but women produce it throughout their lives and actually have more testosterone than estrogen, with levels declining gradually with age, often starting well before menopause itself.

Its best-established, evidence-based clinical use in women remains the treatment of low sexual desire (Davis et al., 2019). But that's not the whole picture. A 2023 systematic review of observational studies examining endogenous testosterone levels found associations between testosterone concentrations and muscle mass, strength, and physical performance in women (Taylor et al., 2023) — an area of research that has historically been underexplored. Testosterone contributes to muscle protein synthesis and strength, plus it's a motivation hormone, motivation to get up and go, to move, all of which are directly relevant to musculoskeletal health.

"If training effort has stayed consistent but the results haven't, testosterone is worth discussing with your provider — not just in the context of libido, but in the context of strength and function."

What You Can Actually Do About It: Hormone Testing, Physiotherapy, and Strength Training in Calgary

The musculoskeletal syndrome of menopause is treatable, and a lot of it is preventable with early intervention. Managing it well usually comes down to two things working together: an accurate picture of your hormones, and a training approach suited to this new hormonal environment.

Start With a Hormone Consultation

A hormone consult can help put your symptoms and hormonal changes into context, including whether testing for estrogen, progesterone, and testosterone is appropriate for you. From there, your care team can use your symptoms, clinical history, and, when appropriate, lab results to guide treatment as you move through perimenopause and into postmenopause.

For women who are good candidates, current clinical guidance supports hormone therapy as a favourable option: for those under 60 or within 10 years of their final period, the benefit-risk balance generally favours symptom relief and bone protection (NAMS 2022 Hormone Therapy Position Statement Advisory Panel, 2022). However, if you are outside of that window, that doesn't necessarily mean you cannot safely take hormone therapy. This is where an individualized consultation is important, to help you understand your unique risk and benefit profile and determine whether hormone therapy is right for you.

Then Build a Body That Can Handle the Transition

Resistance training is one of the most effective tools available here. A 2024 systematic review and meta-analysis found consistent benefits of resistance training on strength, body composition, and physical function in healthy postmenopausal women (González-Gálvez et al., 2024). Strength training does what hormones alone can't:

menopause hormones


Working with a physiotherapist, chiropractor, or strength coach who understands hormone-related musculoskeletal changes makes a real difference here. A generic program built for a 25-year-old's physiology isn't the right fit for a 48-year-old whose estrogen has dropped 40% in two years. Structured, joint-specific rehab — like shoulder, hip, or foot foundation programs — can be especially useful if you're already managing pain or an old injury and need to rebuild strength without aggravating it.

A Team Approach Works Best

Hormone health and musculoskeletal health aren't separate problems; they're the same problem viewed from two angles. That's the premise behind the partnership between Pause Health and Vital Performance Care: Pause Health handles the hormone side — testing, interpretation, and treatment where appropriate — while Vital Performance Care's physiotherapists, chiropractors, and strength coaches handle the movement side, building a program suited to what your body actually needs.

menopause graph


Conclusion

Joint pain, stiffness, muscle loss, and tendon injuries in your 40s and 50s are common. Common doesn't mean normal, and it doesn't mean untreatable. The musculoskeletal syndrome of menopause has a strong hormonal component, and understanding your estrogen, progesterone, and testosterone levels is often a key piece in explaining these changes. Paired with the right strength and rehab program, this is one of the more addressable parts of the menopause transition.

If you're in Calgary and dealing with new aches, stiffness, or strength loss that started around perimenopause, it's worth investigating rather than waiting. Get your hormones tested, get assessed, and build a plan suited to where your body actually is.

Book a Hormone Consult with Pause Health

Book a Clinical Musculoskeletal Assessment with a Chiropractor or Physiotherapist at Vital Performance Care

About the Author

Shelby Sheppard, BN, MN, FNP-C

Shelby Sheppard, BN, MN, FNP-C, is a Nurse Practitioner and the founder of Pause Health (pausehealth.ca), a virtual hormone and sexual health clinic based in Calgary, Alberta. Her practice focuses on hormone health, sexual medicine, and evidence-based menopause care.

Shelby is a community partner of Vital Performance Care, and the practitioners at Vital refer to and rely on Shelby to co-manage complex client cases with.


Pause Health and Menopause Syndrome


References

Critchlow, A. J., Hiam, D., Williams, R., Scott, D., & Lamon, S. (2023). The role of estrogen in female skeletal muscle aging: A systematic review. Maturitas, 178, 107844. https://doi.org/10.1016/j.maturitas.2023.107844

Davis, S. R., Baber, R., Panay, N., Bitzer, J., Cerdas Perez, S., Islam, R. M., Kaunitz, A. M., Kingsberg, S. A., Lambrinoudaki, I., Liu, J., Parish, S. J., Pinkerton, J., Rymer, J., Simon, J. A., Vignozzi, L., & Wierman, M. E. (2019). Global consensus position statement on the use of testosterone therapy for women. Climacteric: The Journal of the International Menopause Society, 22(5), 429–434. https://doi.org/10.1080/13697137.2019.1637079

González-Gálvez, N., Moreno-Torres, J. M., & Vaquero-Cristóbal, R. (2024). Resistance training effects on healthy postmenopausal women: A systematic review with meta-analysis. Climacteric: The Journal of the International Menopause Society, 27(3), 296–304. https://doi.org/10.1080/13697137.2024.2310521

Hansen, M. (2018). Female hormones: Do they influence muscle and tendon protein metabolism? The Proceedings of the Nutrition Society, 77(1), 32–41. https://doi.org/10.1017/S0029665117001951

Karlamangla, A. S., Shieh, A., & Greendale, G. A. (2021). Hormones and bone loss across the menopause transition. Vitamins and Hormones, 115, 401–417. https://doi.org/10.1016/bs.vh.2020.12.016

NAMS 2022 Hormone Therapy Position Statement Advisory Panel. (2022). The 2022 hormone therapy position statement of The North American Menopause Society. Menopause, 29(7), 767–794. https://doi.org/10.1097/GME.0000000000002028

Taylor, S., Islam, R. M., Bell, R. J., Hemachandra, C., & Davis, S. R. (2023). Endogenous testosterone concentrations and muscle mass, strength and performance in women, a systematic review of observational studies. Clinical Endocrinology, 98(4), 587–602. https://doi.org/10.1111/cen.14874

Tehalia, M. K., Agarwal, S., Lalwani, A., & Sharma, S. (2026). Estrogen deficiency in menopause: A major contributor to cartilage degeneration and osteoarthritis: A systematic review and meta-analysis. Journal of Menopausal Medicine, 32(1), 18–29. https://doi.org/10.6118/jmm.25141

Wright, V. J., Schwartzman, J. D., Itinoche, R., & Wittstein, J. (2024). The musculoskeletal syndrome of menopause. Climacteric, 27(5), 466–472. https://doi.org/10.1080/13697137.2024.2380363